Gynecomastia vs Chest Fat: How to Tell the Difference
AI Summary
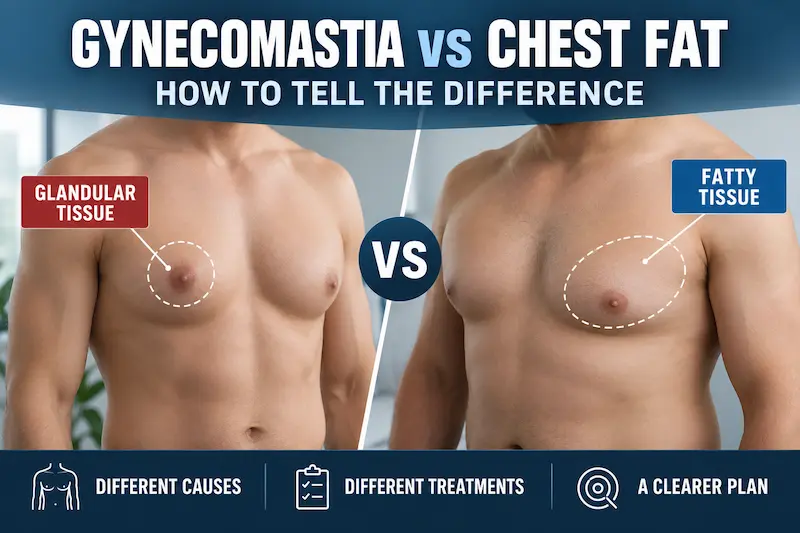
- Gynecomastia vs chest fat separates firm glandular tissue from soft, diffuse fat.
- Treatment depends on tissue type: liposuction for fat, excision for gland.
- A medical exam confirms diagnosis; self-checks guide, but do not replace evaluation.
- Cost planning is safer when based on fat, gland, skin, or mixed tissue.
Summary generated by AI, fact-checked by our medical experts
Gynecomastia vs chest fat comes down to what is creating the fullness: glandular breast tissue, fatty tissue, or a mix of both. Gynecomastia often feels like a firm, rubbery disc under the nipple. Chest fat feels softer and more spread out across the chest. A self-check can guide you, but only a medical exam can confirm the cause.
Many men call both problems “man boobs,” but the treatment path is not the same. Fat-dominant fullness may improve with weight loss or liposuction. Glandular gynecomastia usually does not disappear with dieting because the firm breast gland remains under the areola. If you are comparing your own chest, start with a simple question: does it feel soft and diffuse, or is there a defined lump beneath the nipple?
This guide explains the difference in clear, practical terms. It also shows why AKM Clinic’s gynecomastia surgery assessment focuses on gland, fat, skin quality, and your goals instead of giving every patient the same plan.
Quick answer: Gynecomastia is usually firm glandular tissue under or around the nipple. Chest fat, also called pseudogynecomastia or lipomastia, is soft fatty tissue spread across the chest. If the chest shrinks clearly with weight loss, fat may be the main issue. If a rubbery disc remains under the areola, glandular gynecomastia may be present.
Table of Contents
Gynecomastia vs Chest Fat — What’s Actually Different?
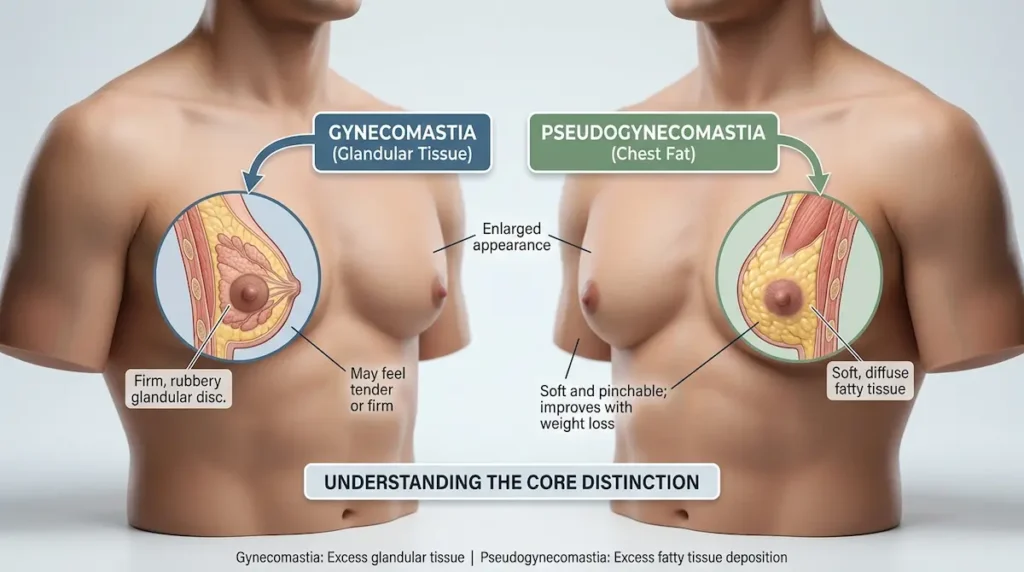
This section explains the core distinction: gynecomastia is a tissue problem, while chest fat is a fat-distribution problem. Both can create a similar outline under a T-shirt, but they behave differently under your fingers, during weight loss, and during treatment planning.
Glandular tissue vs fat
True gynecomastia means there is excess male breast gland tissue. The gland usually sits directly behind the nipple-areola complex. It often feels firmer than surrounding fat, almost like a rubbery button or disc. It may be tender in some men, especially during puberty, hormonal shifts, or medication-related changes.
Chest fat is different. It is soft, pinchable, and spread more evenly across the pectoral area. The medical term often used for this is pseudogynecomastia. Some clinicians also use lipomastia, meaning breast-area fullness caused mainly by fat rather than gland.
The StatPearls clinical review describes pseudogynecomastia as male breast enlargement caused by fat deposition without true glandular proliferation. That is why a careful tissue assessment matters before choosing any procedure. You can review the medical distinction in the StatPearls review of gynecomastia.
Gland does not respond to fat loss the same way fat does. You can lose weight, build your chest, and lower your body-fat percentage, yet still see a puffy nipple or rounded areola if glandular tissue remains.
Why both can look like “man boobs”
From the outside, gynecomastia and chest fat can look nearly identical. A rounded lower chest, a soft fold under the nipple, or a nipple that points through clothing can happen with either condition. That is why appearance alone is not enough.
The clue is how the fullness is distributed. Chest fat usually blends into the upper abdomen, armpit area, and sides of the chest. Gynecomastia is more centered under the nipple. Some men have both, which is common after weight gain, hormone changes, or long-standing chest fullness.
A mixed case can be confusing. The outer chest may feel soft, while the area under the areola feels firmer. In that situation, the question is not simply “is it gyno or fat?” It may be both.
Terms you may hear: gynecomastia, pseudogynecomastia, and lipomastia
These terms are often used loosely online, so here is the practical meaning:
| Term | What it means | How it usually feels | Why it matters |
|---|---|---|---|
| Gynecomastia | Enlarged male breast gland tissue | Firm, rubbery, disc-like tissue under the nipple | Often needs gland removal if surgery is chosen |
| Pseudogynecomastia | Chest fullness caused mainly by fat | Soft, diffuse, pinchable tissue across the chest | May improve with fat loss or liposuction in selected cases |
| Lipomastia | Another term for fat-dominant chest enlargement | Soft fatty fullness without a clear glandular disc | Treatment focuses more on fat reduction than gland excision |
| Mixed gynecomastia | Gland and fat are both present | Soft outer fullness plus a firmer central area | May need both liposuction and gland excision |
One word of caution: you cannot diagnose yourself from a table. The table helps you understand the pattern. A clinician confirms the tissue type with an exam, medical history, and sometimes imaging.
Ready to Schedule Your Gynecomastia?
Our surgery dates fill up quickly due to high international demand. Secure your consultation today to plan your ideal travel dates.
Is It Gyno or Fat? How to Tell at Home Without Diagnosing Yourself?
This section gives you a safe, practical way to assess what you are feeling and seeing. Think of it as a chest fat or gyno test for clues, not a final diagnosis. The goal is to decide whether your chest fullness looks fat-dominant, gland-dominant, mixed, or worth medical review.
Feel: firm rubbery disc vs soft diffuse fat
Stand upright in front of a mirror. Relax your chest. Place your thumb and fingers around the areola and gently press inward, then pinch the tissue beneath and around the nipple. Do not squeeze aggressively.
If you feel a firm, rubbery, round or oval disc directly under the nipple, gynecomastia is more likely. This tissue can feel separate from the softer fat around it. It may be tender, but it is not always painful.
If the tissue feels soft and spread out, especially across the lower chest and toward the armpit, chest fat may be the bigger factor. Fat tends to pinch as a broad layer. It does not usually feel like a defined button beneath the areola.
If what you feel is unclear, do not rely on a single pinch test; a clinical examination is the reliable next step.
“A disc-like firmness under the nipple often changes the plan. If gland is present, liposuction alone may flatten the surrounding fat but leave the central puffiness behind.”
— AKM Clinic board-certified plastic surgery team
Visual clues: puffy nipples and areola changes
Puffy nipples are one of the most common reasons men start researching gynecomastia. The nipple-areola complex may look raised, cone-shaped, or pushed forward even when the rest of the chest is not very fatty.
That does not automatically mean surgery is needed. Puffy nipples can happen from gland, fat, skin looseness, or a combination. Cold temperature, posture, recent exercise, and lighting can also change how the nipple looks.
Look at consistency instead. If the nipple stays puffy in different temperatures, after weight loss, and when your chest muscles are relaxed, glandular tissue becomes more likely. If the puffiness changes mainly with overall body weight, fat may be playing a larger role.
Weight-change test: fat shrinks, gland tends to remain
The weight-change pattern is useful. It is not perfect, but it tells you a lot.
If your chest fullness decreases at the same pace as your stomach, waist, and love handles, chest fat is likely part of the issue. If you lose weight and the surrounding chest becomes flatter but the nipple area still projects, gland may be left behind.
This is why fit men can still have gynecomastia. A low body-fat percentage can reveal the gland more clearly because there is less fat hiding it. The chest may look lean around the pectoral muscle but still rounded at the areola.
If you are wondering how to know if you have gynecomastia, combine three clues: feel, appearance, and weight response. A firm central disc, persistent puffy nipples, and little change after fat loss point more toward glandular gynecomastia. Soft tissue that improves with overall fat loss points more toward pseudogynecomastia.
Common Causes — and When It’s Not Just Fat
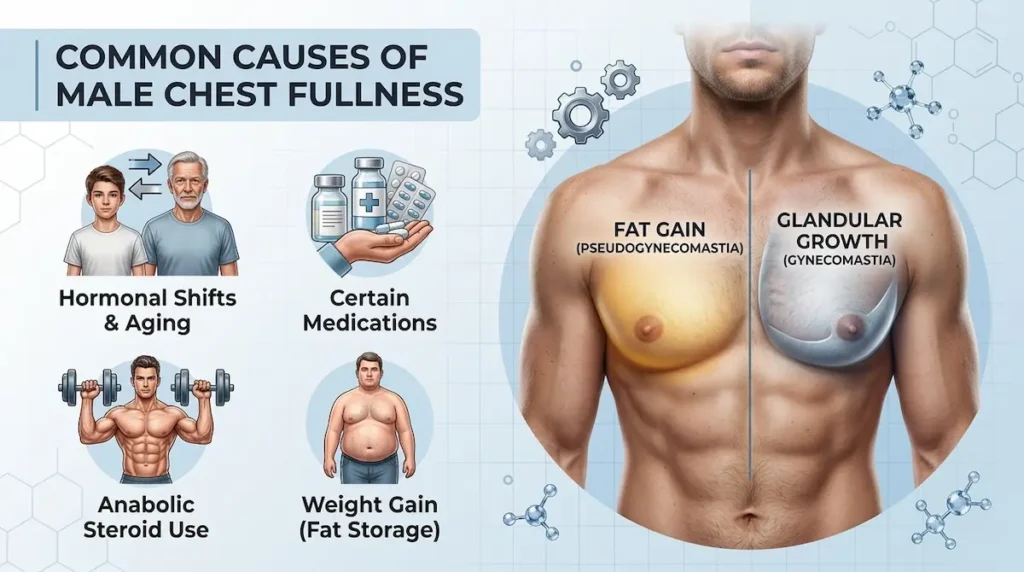
This section explains why male chest fullness can appear in the first place. Fat gain is only one possibility. Hormones, puberty, aging, medications, anabolic steroid use, and certain medical conditions can also affect male breast tissue, which is why persistent or one-sided changes deserve more than a mirror check.
Puberty, aging, and hormone shifts
Gynecomastia often starts during puberty, when testosterone and estrogen balance is changing quickly. For many teens, it improves over time without surgery. For others, the gland remains into adulthood and becomes a long-term source of self-consciousness.
Adult men can also develop gynecomastia later in life. As testosterone levels decline with age and body fat increases, estrogen activity can become more noticeable. That shift may stimulate breast gland tissue. The result can look like ordinary chest fat, but the central firmness tells a different story.
There is also a feedback loop. More body fat can increase estrogen conversion in fat tissue. That may make chest fat and glandular fullness appear together. This is one reason glandular vs fatty gynecomastia is not always an either-or question.
Medications, steroids, and weight gain
Several medication groups have been associated with gynecomastia. These can include some anti-androgens, anabolic steroids, certain heart medications, some psychiatric medications, and drugs that affect hormone metabolism. Do not stop a prescribed medication on your own. Talk with the clinician who prescribed it.
Anabolic steroid use is a common trigger in men who lift weights. The chest may be muscular, the body fat may be low, yet the nipple area stays puffy because gland tissue has developed. In that setting, more bench press will not remove the gland.
Weight gain can create a different pattern. The chest becomes softer and broader, and fullness often appears along the sides of the chest as well. If the tissue reduces with overall fat loss, pseudogynecomastia may be the stronger factor. If the chest stays pointed or puffy at the areola, gland may still be present.
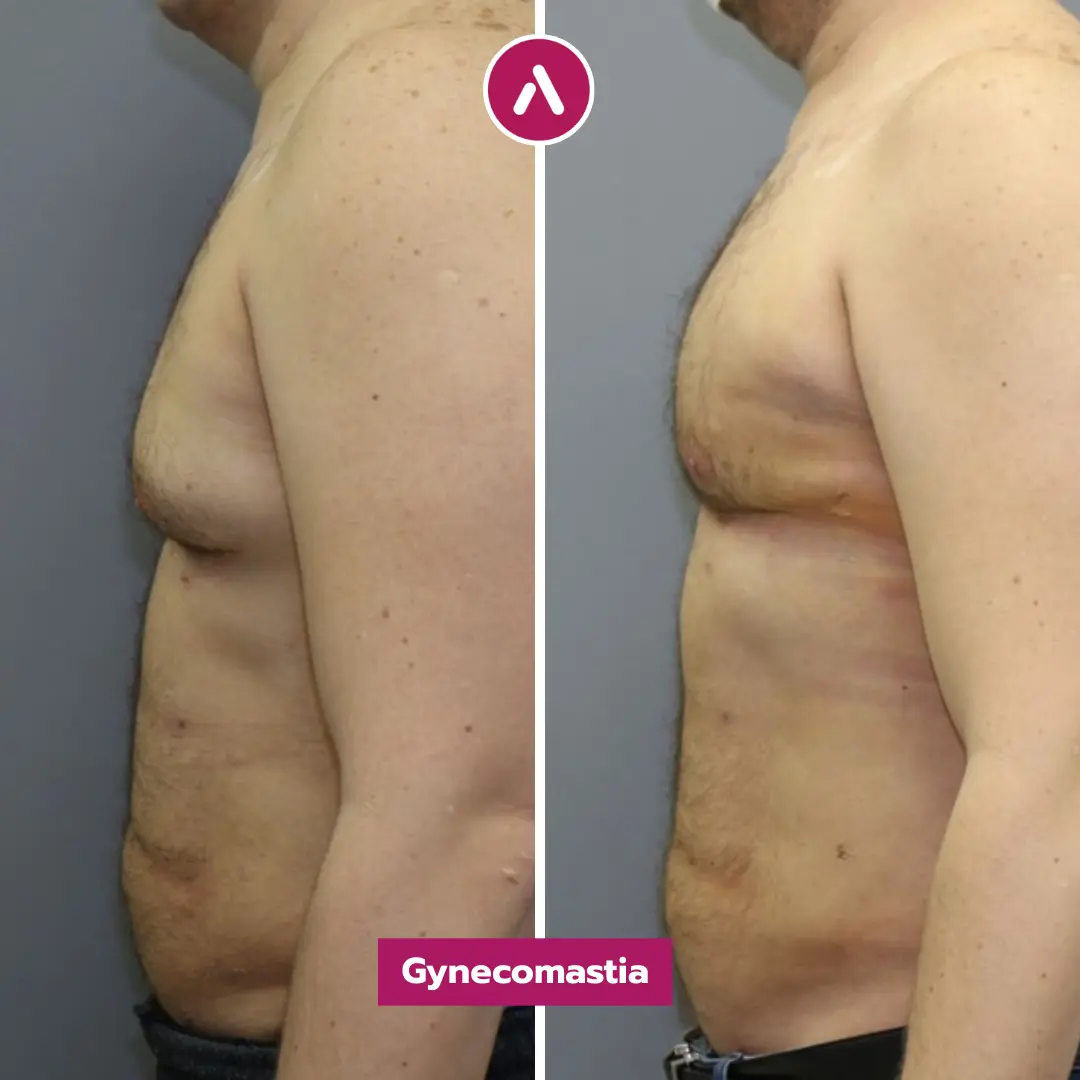
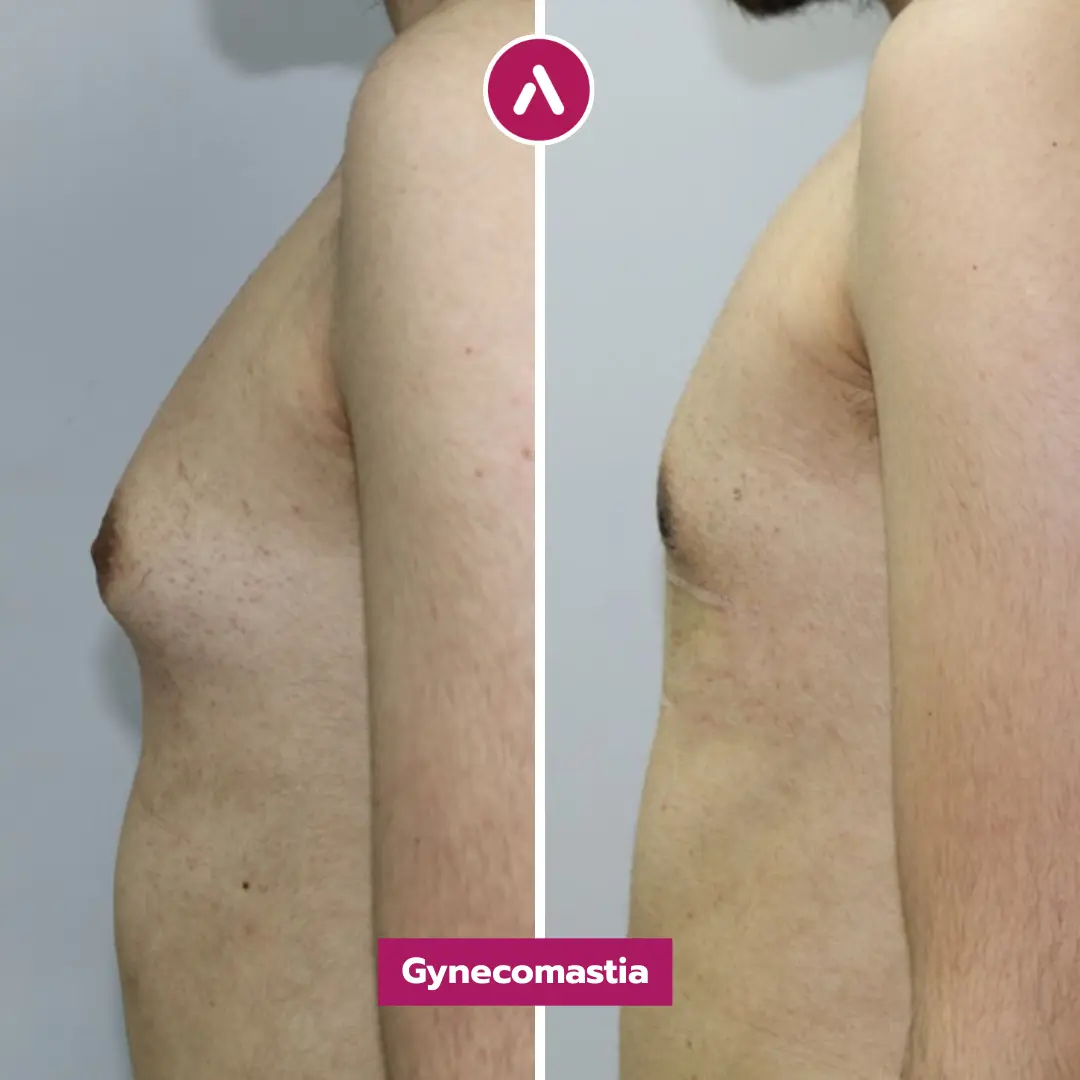
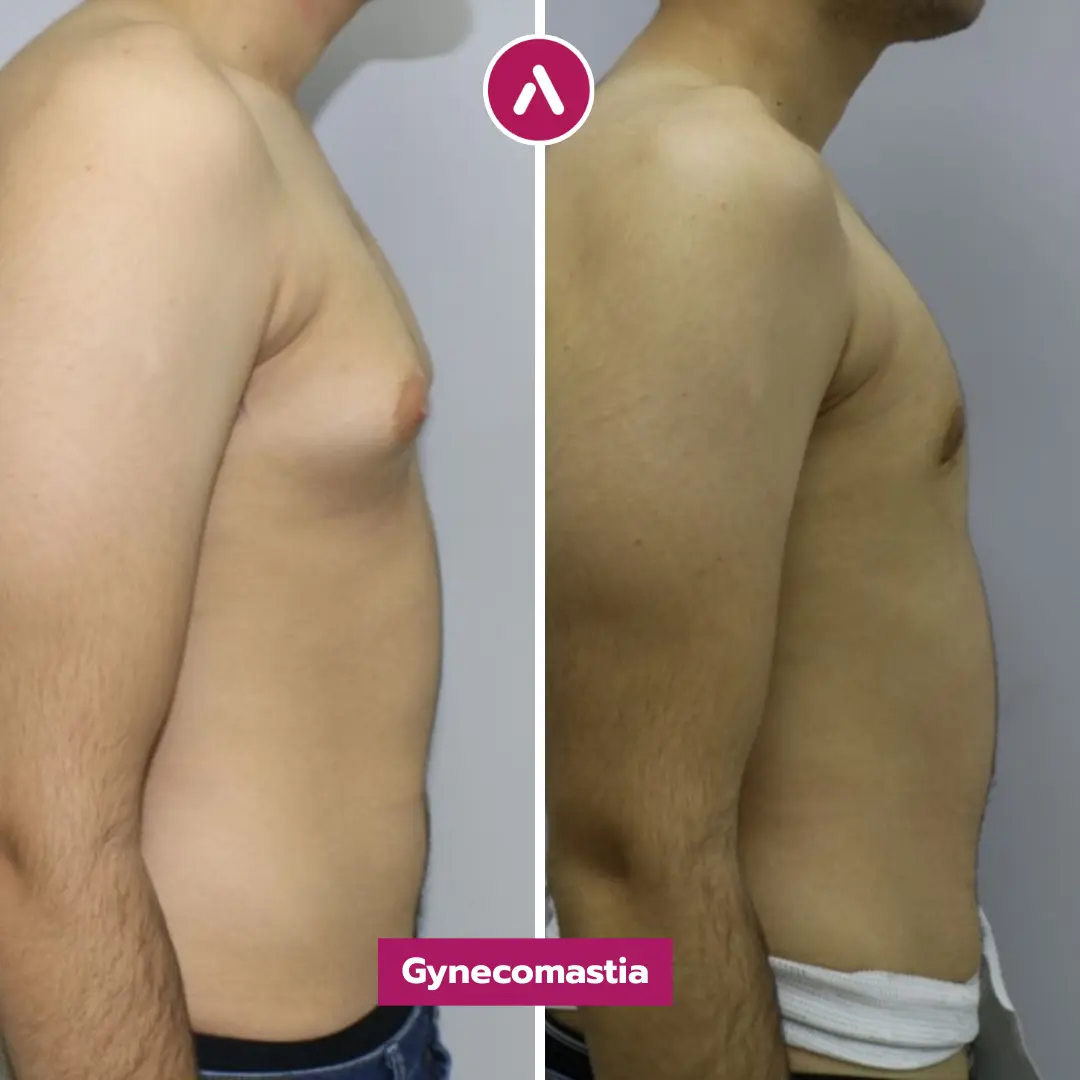
Red flags: one-sided hard lump, discharge, or rapid growth
Most male chest fullness is benign, but some signs should be checked promptly. A new hard lump on one side, nipple discharge, skin dimpling, nipple inversion, bleeding, or rapid growth is not something to “wait out” with dieting.
Gynecomastia is usually centered beneath the nipple and can affect one or both sides. A suspicious lump may feel different: harder, irregular, fixed, or off-center. Pain is not the only warning sign. Some concerning changes are painless.
If you notice any of these signs, schedule an in-person medical evaluation before considering cosmetic treatment. A plastic surgery consultation is not a substitute for primary care, endocrine workup, breast imaging, or other tests when red flags are present.
Everything You Need to Know About Gynecomastia
From surgery steps to aftercare, get all the details on how AKM Clinic performs world-class Gynecomastia in Istanbul.
Why the Difference Changes Your Treatment
This section connects the diagnosis clues to real treatment choices. The main decision is not simply “remove the chest.” It is whether the fullness is fat, gland, loose skin, or a combination. Each tissue type responds to a different approach.
Fat-dominant cases may respond to liposuction
If the problem is mostly fatty tissue, liposuction may be enough in selected patients. Liposuction removes fat through small cannula entry points. It can flatten the chest and blend the lower pectoral contour when skin quality is good.
But liposuction cannot remove a dense glandular disc effectively. A cannula can reduce surrounding fat, yet a firm central mound may stay behind. This is why some men feel disappointed after lipo-only treatment for what was actually gland-dominant gynecomastia.
The same principle applies in other body areas: liposuction is designed for fat, not gland or loose skin. For comparison, AKM’s guide to how liposuction treats other stubborn fat zones explains why localized fat behaves differently from structural tissue.
Glandular tissue usually needs excision
If a firm gland sits beneath the nipple, excision is usually the key step. Excision means the surgeon removes dense glandular tissue through a carefully placed incision, often near the areola border. The goal is a flatter chest without leaving a crater or sharp edge.
That step requires judgment. Removing too little gland can leave puffy nipples. Removing too much can cause a hollow or stuck-down areola. A board-certified plastic surgery team plans the gland removal, surrounding fat blending, and skin behavior together.
Scars are part of that discussion. They are usually placed around the areola or in small liposuction entry sites, depending on the plan. Your surgeon can explain how those scars are likely to heal in your case; this article does not go into a scar timeline.
Mixed cases and realistic outcomes
Many men are not purely one category. A common pattern is soft fat across the lower chest with a firmer disc under the areola. Another pattern is gland plus stretched skin after major weight loss. These mixed cases need a combined plan.
The grading system helps surgeons describe severity, skin excess, and the likely treatment route. Our gynecomastia surgery in Turkey page explains how severity grading changes the surgical plan. Here, the key point is simpler: tissue type drives treatment.
| What seems dominant? | Typical clues | Weight-loss response | Common treatment direction |
|---|---|---|---|
| Chest fat / pseudogynecomastia | Soft, broad, pinchable fullness across the chest | Often improves as body fat decreases | Weight loss first; liposuction may help selected patients |
| True gynecomastia | Firm or rubbery disc under the nipple, often with puffy areola | May remain after fat loss | Gland excision is often needed if surgery is chosen |
| Mixed gland and fat | Soft outer fullness plus central firmness | Fat improves, nipple projection may remain | Liposuction plus gland excision may be considered |
| Gland, fat, and loose skin | Drooping chest, stretched areola, lower fold, skin laxity | Weight loss can make skin looseness more visible | May require skin management as well as fat and gland correction |
The American Society of Plastic Surgeons describes this same treatment logic: liposuction techniques may be used when excess fatty tissue is the main issue, while excision is used when glandular breast tissue or excess skin must be removed. You can review ASPS guidance on gynecomastia surgery techniques for the lipo-versus-excision distinction.
AKM planning note: For US patients traveling to Istanbul, the first step is not choosing liposuction or excision from a menu. The safer path is a photo-based pre-assessment, a medical history review, and confirmation during the in-person exam. The plan should answer one question clearly: is your chest fat, gland, skin, or a mix?
What to Do Next?
This section turns the comparison into a practical next step. Once you understand the likely difference between fat, gland, and mixed tissue, the next move is not guessing a procedure. It is getting the chest examined, asking the right questions, and making sure the treatment plan matches the tissue type.
Start with an exam, medical history, and sometimes imaging
A proper assessment starts with your history. Your surgeon or physician should ask when the chest fullness started, whether it changed with weight, whether it is painful, and whether you use any medications, supplements, or anabolic steroids. This matters. The cause can change the recommendation.
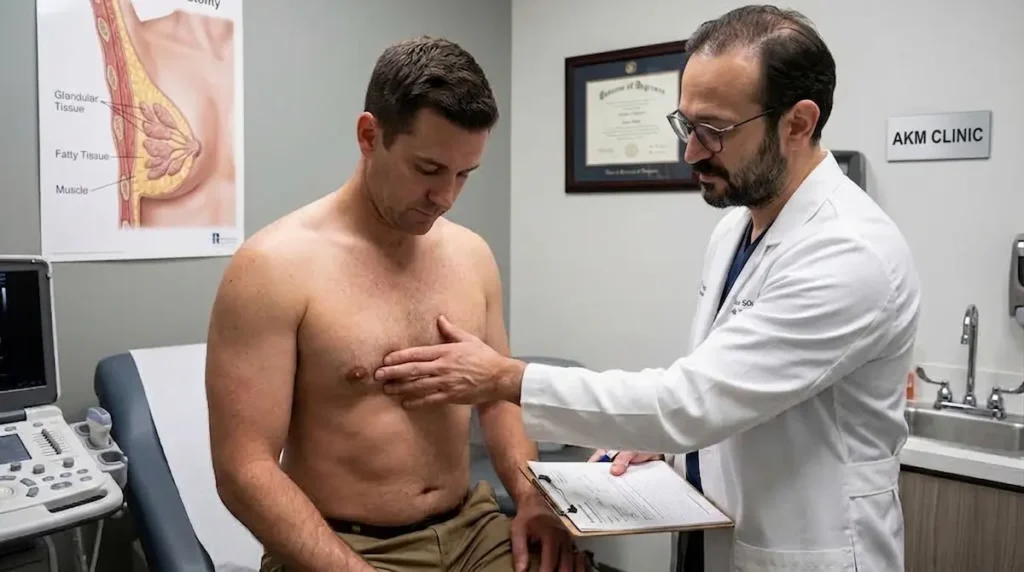
Next comes a physical exam. The clinician checks the tissue under the nipple, the amount of soft fat across the chest, skin elasticity, nipple position, and symmetry. If the finding is unclear, or if there are warning signs, ultrasound or further medical evaluation may be needed before cosmetic planning.
Photos can help with pre-assessment, especially for international patients. They cannot replace touch. A photo may show puffy nipples or a rounded chest, but it cannot confirm whether the tissue is firm gland, soft fat, or both. That confirmation happens during the in-person exam.
Questions to ask before choosing treatment
Before you decide on surgery, ask specific questions. Broad promises are not helpful. You want answers that describe your anatomy.
- Do I have fat, glandular tissue, loose skin, or a mix?
- Would liposuction alone leave central nipple puffiness?
- Would gland excision be needed under the areola?
- How will the chest be blended so it does not look hollow?
- Where would the scars sit, and how visible are they likely to be?
- What grade of gynecomastia do I have?
- Do any symptoms need medical evaluation before cosmetic surgery?
These questions help you avoid the common mistake of treating every male chest as a fat problem. They also help you understand why two men with similar-looking chests may need different plans.
Cost logic without opening pricing detail
Cost depends on the treatment plan. A fat-dominant case, a gland-dominant case, and a mixed case do not involve the same surgical steps. Skin excess can also change the plan. That is why pricing should be tied to diagnosis, not just the phrase “male chest reduction.”
Because this article is focused on the difference between gynecomastia and chest fat, it will not turn into a price guide. For that, use AKM’s dedicated page on gynecomastia surgery pricing. It keeps the cost discussion separate from the diagnostic question.
If your main concern is “I cannot tell what this is,” start with the tissue assessment. Once the team knows whether the fullness is fat, gland, skin, or mixed, the procedure plan and quote become much more meaningful.
Considering treatment? Ask AKM whether your chest is fat, gland, or both — and what that means for treatment. A virtual consultation can help you understand whether liposuction, gland removal, or a combined approach is worth discussing in person.
Frequently Asked Questions: Gynecomastia vs Chest Fat
This section answers the most common questions men ask after checking their chest at home. The answers are practical, but they are not a diagnosis. If you have pain, a one-sided hard lump, discharge, skin changes, or rapid growth, arrange a medical evaluation first.
How do I know if I have gynecomastia or just chest fat?
Can chest fat look like gynecomastia?
Does gynecomastia go away with weight loss?
Is it gyno or fat if it’s soft?
Can liposuction treat gynecomastia?
When should I see a doctor about male breast tissue?
Can exercise fix puffy nipples?
What is the best test for gynecomastia vs chest fat?
Final takeaway: The gynecomastia vs chest fat question is really a tissue question. Fat feels soft and often changes with weight. Gland feels firmer and tends to remain under the nipple. Once you know which tissue is causing the fullness, treatment planning becomes clearer, safer, and more realistic.
Have Specific Questions About Gynecomastia?
Chat directly with our dedicated patient coordinators regarding Gynecomastia. Get instant answers and personalized support.
Medical disclaimer: This article is for educational purposes only and does not replace medical advice, diagnosis, or treatment. Results and recovery vary by patient. If you have pain, nipple discharge, a hard lump, rapid growth, or skin changes, seek medical evaluation before considering cosmetic surgery.
Related Treatments
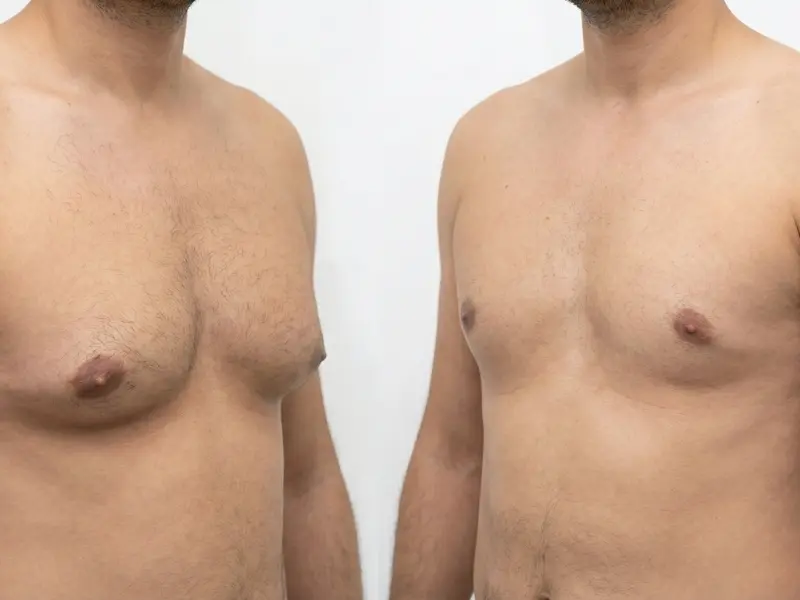
Awake Gynecomastia Surgery in Turkey
Awake gynecomastia guide: local anesthesia vs general, technique options, recovery timeline, risks, and cost/value insights for expert patients.
Awake Abdominal Etching in Turkey
Learn what awake abdominal etching is, who it’s for, recovery timeline, risks, and USA vs Turkey value—plus how to choose a qualified surgeon.
Awake Tummy Tuck in Turkey
Learn how an awake tummy tuck works, who qualifies, anesthesia options, step-by-step surgery, recovery timeline, risks, scars, and cost comparison.
Sapphire Hair Transplant in Turkey
Learn how Sapphire Hair Transplant uses sapphire blades for precise channels, natural hairlines, and a clear recovery timeline—plus cost/value in Turkey.
Ready to Start Your Own Transformation Journey?
Join the 2,000+ patients who trusted Dr. Akif Mehmetoğlu and the AKM Clinic team. Your journey to a more confident, revitalized you begins with a simple, no-obligation conversation. Contact us today from the USA for your free virtual consultation.
#1: Get Your Free Personalised Quote
Start with a free, no-obligation online consultation. Share your photos, and our surgical team will provide a fully personalised treatment plan and a transparent, all-inclusive price package. No hidden fees.
#2: Secure Your Date & VIP Booking
Once you're ready, our dedicated patient coordinators will help you secure your procedure date. We'll handle all your bookings, including your 5-star hotel and private VIP airport transfers.
#3: Arrive in Istanbul & Meet Your Surgeon
Arrive at Istanbul Airport (IST) and be greeted by your private driver. Settle into your hotel and prepare for your in-person consultation, where you'll meet your specialist surgeon to finalise the details for your "natural, subtle, and revitalized" new look.